How an Emergency Dentist Handles Same-Day Extractions

A same-day extraction sits at the intersection of urgency, judgment, and pain control. People usually arrive at an emergency dental visit because something has tipped from manageable to impossible. A cracked molar has split below the gumline during lunch. A wisdom tooth infection has swollen overnight and made swallowing painful. A loose tooth from trauma is hanging on by tissue and every bite sends a sharp jolt through the jaw. At that point, the question is rarely academic. It is immediate: can this tooth be saved, or does it need to come out today?
An Emergency Dentist makes that call under pressure, but not casually. Same-day extraction is not the default answer to every dental emergency. It is a specific treatment choice, used when removing the tooth is the safest, fastest, or most predictable way to stop pain, control infection, or prevent a larger problem. In practice, the decision depends on the condition of the tooth, the surrounding bone and gum tissue, the patient’s medical history, and how quickly the person needs relief.
For patients, the process often feels abrupt. For the clinician, it is deliberate. Even in an urgent setting, the extraction follows a careful sequence: evaluation, imaging, anesthesia, removal, bleeding control, and a very clear plan for healing. When that sequence is handled well, the appointment can feel surprisingly orderly, even when the patient walks in distressed.
When a tooth needs to come out the same day
There is a difference between a tooth that hurts and a tooth that cannot reasonably wait. Dentists see both. Some emergencies can be stabilized with medication, temporary treatment, or referral for follow-up. Others are already beyond repair or are creating risks that grow with every hour.
A tooth may need same-day extraction when the decay is so deep that too little healthy structure remains for a crown or filling to hold. Another common situation is a vertical fracture that extends into the root. Those fractures often look small from the outside, yet they create pain with biting and open a pathway for infection that rarely responds to patchwork repairs. Advanced periodontal disease can also leave a tooth so loose that chewing becomes unsafe and painful. In trauma cases, the damage may be obvious, especially when the tooth is displaced, broken at the gumline, or associated with a bone injury.
Infections deserve special respect in emergency dentistry. Not every infected tooth must be extracted immediately, but spreading infection changes priorities. If swelling is progressing, the area is difficult to numb because of inflammation, or the patient cannot function due to pain and pressure, extraction may be the cleanest way to remove the source. In some cases, especially around wisdom teeth or heavily decayed molars, a root canal is either not practical or not predictable enough to justify delaying definitive care.
Here are some situations that often push the decision toward same-day removal:
- The tooth is fractured below the gumline or split through the root.
- Decay has destroyed too much tooth structure for reliable restoration.
- The tooth is causing or sustaining a significant infection or abscess.
- Trauma has left the tooth unstable, non-restorable, or painful to even light contact.
- Severe gum disease has made the tooth excessively mobile and uncomfortable.
Those scenarios are common, but there is still nuance. A front tooth, for example, gets a different level of caution because appearance matters and replacement planning starts immediately. A wisdom tooth with partially erupted gum tissue may need extraction because recurrent infection keeps flaring. A lower molar with a deep cavity may technically be saveable, but if the patient has limited finances, repeated infections, or poor long-term prognosis, removal can be the more honest recommendation. Good emergency care is not just about what is possible. It is about what is realistic and durable.
The first few minutes matter more than most patients realize
Emergency visits often begin with a compressed but important triage. Before anyone reaches for forceps, the dentist needs to know what happened, how quickly symptoms developed, what medications the patient takes, and whether there are conditions that affect bleeding, infection risk, or anesthesia.
That initial conversation can change the treatment plan. A patient taking blood thinners may still be a candidate for extraction, but the technique for bleeding control needs more planning. Someone with uncontrolled diabetes may heal more slowly and have a higher infection risk. A person with a history of difficult numbing, panic attacks during dental treatment, or recent facial swelling may need a different pacing and anesthesia strategy. Pregnancy, bisphosphonate use, immune suppression, recent heart procedures, and active sinus symptoms can all shape the decision.
Pain level is important, but pattern matters just as much. Throbbing pain that keeps a patient awake suggests inflammation inside or around the tooth. Sharp pain on biting often points to a crack. Swelling near the jawline, a bad taste in the mouth, fever, or difficulty opening widely suggest infection is involved. If there was trauma, the dentist looks for more than the obvious broken tooth. Lip lacerations, jaw tenderness, changes in bite, and missing tooth fragments can all signal a broader injury.
None of this takes long in an emergency setting, but it is not optional. Efficient does not mean rushed.
Why X-rays are part of the decision, even when the tooth seems obviously hopeless
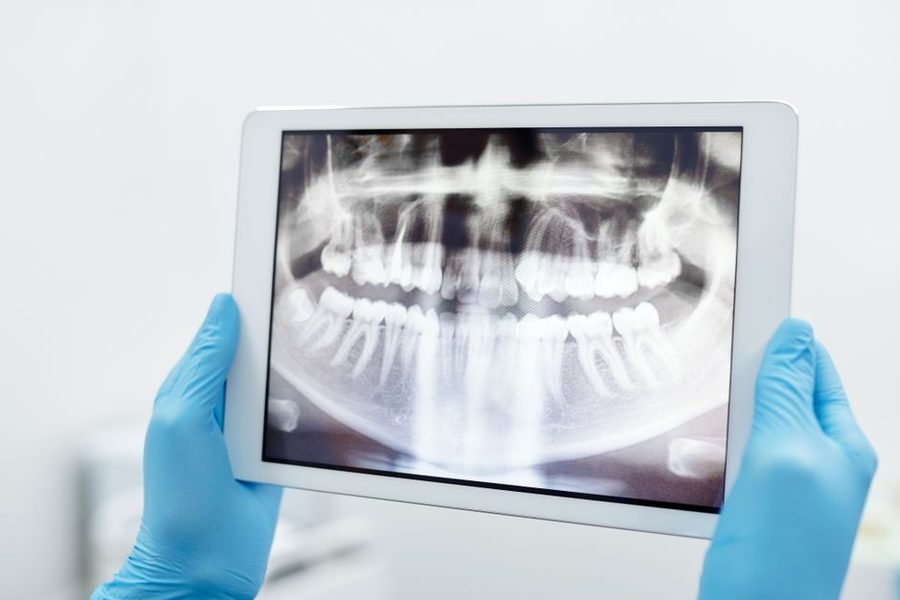
Patients sometimes wonder why imaging is needed when the problem tooth is plainly visible. The reason is simple: teeth fail in three dimensions, and extraction is safer when the dentist knows what lies under the gum.
A periapical X-ray or panoramic image can reveal root shape, length, curvature, infection at the tip of the root, bone loss, retained roots, or proximity to nearby structures such as the maxillary sinus or the inferior alveolar nerve. Lower wisdom teeth, in particular, require careful imaging because the roots may sit close to the nerve canal. A tooth that looks easy above the gum can become a more technical extraction once the roots are seen.
Imaging also confirms whether the tooth is actually the source of the pain. It is not unusual for patients to point to one tooth while the real problem is the neighbor. Referred pain from upper molars can be misleading. So can clenching-related pain or a cracked tooth that does not show an obvious cavity. Removing the wrong tooth is one of the most serious avoidable errors in dentistry, and radiographs help prevent it.
In everyday practice, imaging often settles the central question quickly. If the X-ray shows a large cavity extending below the bone, a root fracture, or widespread bone loss around a loose tooth, the case for extraction becomes much stronger. If the roots are intact and the tooth is restorable, the emergency dentist may stabilize the situation and refer for endodontic or restorative care instead.
Numbing the area is both science and technique
Patients usually fear two things about extraction: the injection and the moment the tooth comes out. In experienced hands, the actual extraction is often less uncomfortable than expected. The hard part is achieving profound anesthesia in an inflamed area.
Inflamed tissue has a lower pH, which can reduce how well local anesthetic works. That is why a badly infected lower molar may remain stubbornly sensitive even after an injection that would fully numb a routine case. Emergency dentists know this pattern and adjust. They may use a nerve block plus supplemental infiltration, intraligamentary anesthesia around the tooth, or additional time for the anesthetic to take effect. Sometimes pacing helps as much as pharmacology. Giving the first injection slowly, allowing time for onset, then testing the area properly can spare the patient a rough experience.
Topical anesthetic also matters more than people think. It does not numb the tooth, but it can make the soft tissue injection easier. A calm explanation helps too. Tense patients often brace, hold their breath, or assume pressure means pain. Clear communication changes that. A dentist might say, “You will feel pushing and pressure, but you should not feel sharp pain. If you do, raise your hand and we stop.” That simple agreement builds control into an otherwise stressful visit.
Sedation is not always available or necessary in emergency care, but for some patients it changes everything. Oral sedation or nitrous oxide can help those with severe anxiety, strong gag reflexes, or traumatic dental history. Even without sedation, a measured approach to anesthesia is one of the biggest markers of quality in same-day extraction care.
Simple extraction versus surgical extraction
Not every extraction is the same procedure. That distinction is often lost on patients because both end with the tooth being removed. Clinically, though, there is a significant difference between a simple extraction and a surgical extraction.
A simple extraction is used when the tooth is visible and can be removed with elevators and forceps after loosening it in the socket. This is common with many broken-down teeth that still have enough shape to grasp, as well as some loose teeth with advanced gum disease. It sounds straightforward because, sometimes, it is.
A surgical extraction involves an incision in the gum, removal of some surrounding bone, sectioning the tooth into pieces, or all three. This becomes necessary when the tooth is impacted, fractured at the gumline, ankylosed, or has roots that resist routine removal. Lower molars and wisdom teeth are frequent surgical cases, especially when the crown has crumbled and there is little to hold onto. Surgical does not necessarily mean dangerous. It usually means the dentist is using a more controlled method instead of forcing a difficult tooth out in one piece.
That judgment call matters. Excessive force is not a badge of skill. It is often a sign that the plan needs to change. A careful clinician will stop, reassess, and section the tooth if that will reduce stress on the bone and lower the risk of complications.
What happens during the extraction itself
Once the area is numb, the dentist isolates the tooth, checks anesthesia again, and begins to loosen the attachment between the tooth and the bone. For a simple extraction, elevators are often used first to create mobility. Forceps then apply controlled pressure in specific directions that expand the socket slightly and break the periodontal ligament fibers holding the root in place. The tooth is not pulled like a nail from wood. It is rocked, rotated when anatomy allows, and delivered with gradual force.
For a surgical extraction, the dentist may reflect a small gum flap to improve visibility. If the roots are divergent or the crown is too compromised, the tooth can be sectioned so each root is removed separately. This often feels to the patient like pressure and vibration rather than pain, assuming anesthesia is adequate. The sound can be unsettling, but the tissue handling is usually gentler than one-piece removal would be.
There are always small decisions happening in real time. If a root tip fractures, the dentist weighs whether chasing a tiny, deeply embedded fragment would cause more trauma than leaving it. If granulation tissue from chronic infection fills the socket, it needs to be debrided. If the socket walls are thin and brittle, preservation of bone becomes part of the technique, especially if future implant placement is likely.
In most routine emergency extractions, active removal may take anywhere from a few minutes to half an hour. Difficult impacted teeth can take longer. The visible clock time means less than the quality of the execution.
Bleeding control is part of the procedure, not an afterthought
Once the tooth is out, the work is not over. The socket has to be inspected, cleaned as needed, and stabilized for clot formation. That blood clot is the first stage of healing. If it dislodges too soon, the patient can develop dry socket, a very painful condition that is common enough after difficult extractions, especially in lower molars and in smokers.
Bleeding is usually controlled with direct pressure, gauze, and time. If needed, the dentist may place a hemostatic material into the socket or use sutures to help secure the area. Patients on anticoagulants, those with liver disease, or people with uncontrolled hypertension may need a bit more chairside management, but many extractions still proceed safely with proper local measures.
One common misconception is that a completely dry gauze pack is the goal. It is not. Some oozing is normal for several hours. The goal is steady clotting, not a perfectly blood-free mouth right away. Setting expectations here reduces a lot of evening panic calls.
Cases that need extra caution
Emergency dentistry is full of edge cases. That is where experience shows.
Upper molars can sit close to the sinus. If the roots are long and the bone between the root tip and the sinus floor is thin, extraction carries a small risk of creating an opening between the mouth and the sinus. Lower wisdom teeth raise concern about the inferior alveolar nerve and the lingual nerve, particularly when imaging suggests close proximity. Severely infected tissue may not numb easily and may be too swollen for ideal access. Teeth that have had prior root canal treatment can be brittle and more likely to fracture during removal. Dense bone, common in some younger patients, can make an extraction more technical than the tooth’s appearance suggests.
Medical complexity also changes the workflow. A patient with a prosthetic heart valve or a history of infective endocarditis may require antibiotic considerations based on current guidelines and the planned procedure. Someone with active chemotherapy treatment may need coordination with their medical team. A patient with limited ability to open due to swelling or jaw dysfunction may be safer with specialist involvement if the extraction looks difficult.
A responsible Emergency Dentist knows when to treat immediately and when to refer the same day to an oral surgeon or hospital-based service. That is not hesitation. It is good judgment. If an airway issue is developing, if the infection is spreading into fascial spaces, or if the anatomy makes nerve injury risk unusually high, the best care may happen outside a standard dental office.
The conversation patients remember after the tooth is gone
People tend to remember the instructions they were given only if those instructions were plain, brief, and tied to what they are likely to feel that evening. Dense aftercare speeches fade fast, especially when the patient has been anxious or numb for an hour. Good emergency dentists keep it practical.
The key messages usually cover bleeding, pain control, swelling, eating, oral hygiene, and warning signs. A patient should know that firm pressure on gauze helps, that vigorous rinsing too early can disrupt the clot, and that soreness tends to peak after the anesthetic wears off and into the next day. Ice is often helpful in the first 24 hours for swelling. Soft foods make sense not because they are mandatory forever, but because a hot, crunchy meal on a fresh socket is a bad experiment.
The instructions that matter most often fit on one short checklist:
- Bite on gauze as directed and replace it only if bleeding continues.
- Avoid smoking, straws, forceful spitting, and hard rinsing for the first day.
- Take prescribed or recommended pain medication before the numbness fully wears off.
- Eat soft, lukewarm foods and chew away from the extraction site.
- Call if bleeding is heavy, swelling worsens rapidly, or fever and severe pain develop.
Those details sound basic, but they prevent a surprising number of complications. I have seen patients do beautifully after a difficult extraction because they followed simple instructions closely. I have also seen relatively easy cases turn into miserable recoveries because someone chain-smoked that evening or rinsed aggressively every hour.
Pain after extraction, and what is normal
Patients often assume that if the tooth was the source of severe pain, relief will be instant and complete. Sometimes it is. More often, the character of the pain changes. The deep pressure, throbbing, or infected ache is gone, but a post-surgical soreness takes its place for a few days.
That is normal. A fresh extraction site is a wound, and wounds hurt while they heal. The first 24 to 72 hours usually bring the most discomfort and swelling. Most patients do well with a combination of anti-inflammatory medication and acetaminophen when medically appropriate, though prescriptions vary by case and medical history. Opioids are far less central to routine extraction recovery than they once were, especially because many dental pain patterns respond better to anti-inflammatory strategies.
Dry socket is the complication patients hear about most, and with reason. It is painful, usually starting a few days after extraction, and more common in lower back teeth. The https://maps.app.goo.gl/4o6QHAKDQnEHvxSE7 pain is often described as deep, radiating, and not relieved much by standard medication. It is not usually an infection, and antibiotics do not fix it. The treatment is local care, often with soothing socket dressings and follow-up. Preventing it is easier than treating it, which is why the first-day instructions matter so much.
Planning for what comes next
Same-day extraction solves the emergency, but it opens the question of replacement. That conversation may happen briefly at the urgent visit or later once the patient is comfortable. Either way, it should happen.
Some missing teeth can be left alone without major consequences, especially certain wisdom teeth or teeth that had no functional partner. Many others should be replaced to preserve chewing function, speech, appearance, or tooth position. Options usually include an implant, a bridge, or a removable partial denture, depending on the location of the tooth, the condition of neighboring teeth, the amount of bone, timeline, and budget.
For front teeth, temporization matters quickly. Even a simple temporary appliance can make a big difference in confidence. For molars, timing is often less cosmetic but still important functionally. Bone resorption begins after extraction, and while it is a normal biologic process, it affects future implant planning. In certain cases, socket preservation grafting may be discussed at the emergency visit if the situation is clean enough and the patient is prepared for that added step. In other urgent cases, especially with active infection or financial constraints, the focus stays on safe removal and uncomplicated healing first.
That larger treatment plan is one reason a well-run emergency appointment does not feel isolated. The best same-day extractions relieve the immediate problem while protecting future options.
Why experience changes the outcome
Two patients can present with what sounds like the same emergency and have very different appointments. One has a decayed tooth with straight roots, good access, and no major medical issues. The other has the same degree of pain but a lower molar with curved roots, acute infection, trismus, and a history of difficult anesthesia. On paper, both need extraction. In the chair, they are entirely different cases.
Experience shows up in small choices. Which radiograph gives the clearest view. When to add more anesthetic and where. Whether to section early or try a simple removal first. How to support the jaw during lower extractions. When a fractured root tip should be retrieved and when it should be left. Whether the patient’s swelling is dental and localized or the start of something more serious. Those judgments are hard to teach from a script. They come from treating many mouths, seeing many variations, and respecting the fact that emergencies do not follow neat patterns.
For patients, that experience often translates into something simple: the visit felt calmer than expected. Pain was controlled. The dentist explained the why, not just the what. The tooth came out with less drama than feared. The aftercare made sense. That is what competent emergency extraction care should look like. Not theatrical speed, not pressure to choose treatment blindly, but a focused, informed response to a problem that genuinely needs attention now.
When same-day extraction is the right answer, it can be one of the most direct forms of relief dentistry offers. A tooth that has caused sleepless nights, swelling, foul taste, or sharp pain with every bite can stop dominating the patient’s day in a single appointment. The key is that the decision is earned through examination, imaging, and clinical judgment, then carried out with skill. That is how an Emergency Dentist handles the urgency without letting urgency handle the care.
Smyle Dental Bakersfield
2016 E St, Bakersfield, CA 93301, United States
+16614939040
FAQ About Emergency Dentist
What counts as a dental emergency?
Severe tooth pain, facial swelling, uncontrolled bleeding, a knocked-out or displaced tooth, and significant dental trauma may need prompt assessment. Trouble breathing or rapidly increasing swelling requires urgent medical help.
What should I do if a permanent tooth is knocked out?
Handle the tooth by the crown rather than the root, keep it moist, and contact a dentist immediately. Fast treatment can improve the chance of saving the tooth.
Can an emergency dentist treat severe tooth pain the same day?
Same-day care may be available depending on the cause and schedule. The dentist will examine the area, may take digital X-rays, and recommend treatment based on the diagnosis.
Should I go to the emergency room for dental swelling?
Seek urgent medical care for trouble breathing, difficulty swallowing, rapidly spreading facial swelling, or other severe symptoms. A dentist can assess the underlying dental cause and provide appropriate follow-up care.